A prescription upload, a test booking and a consultation need three different decisions
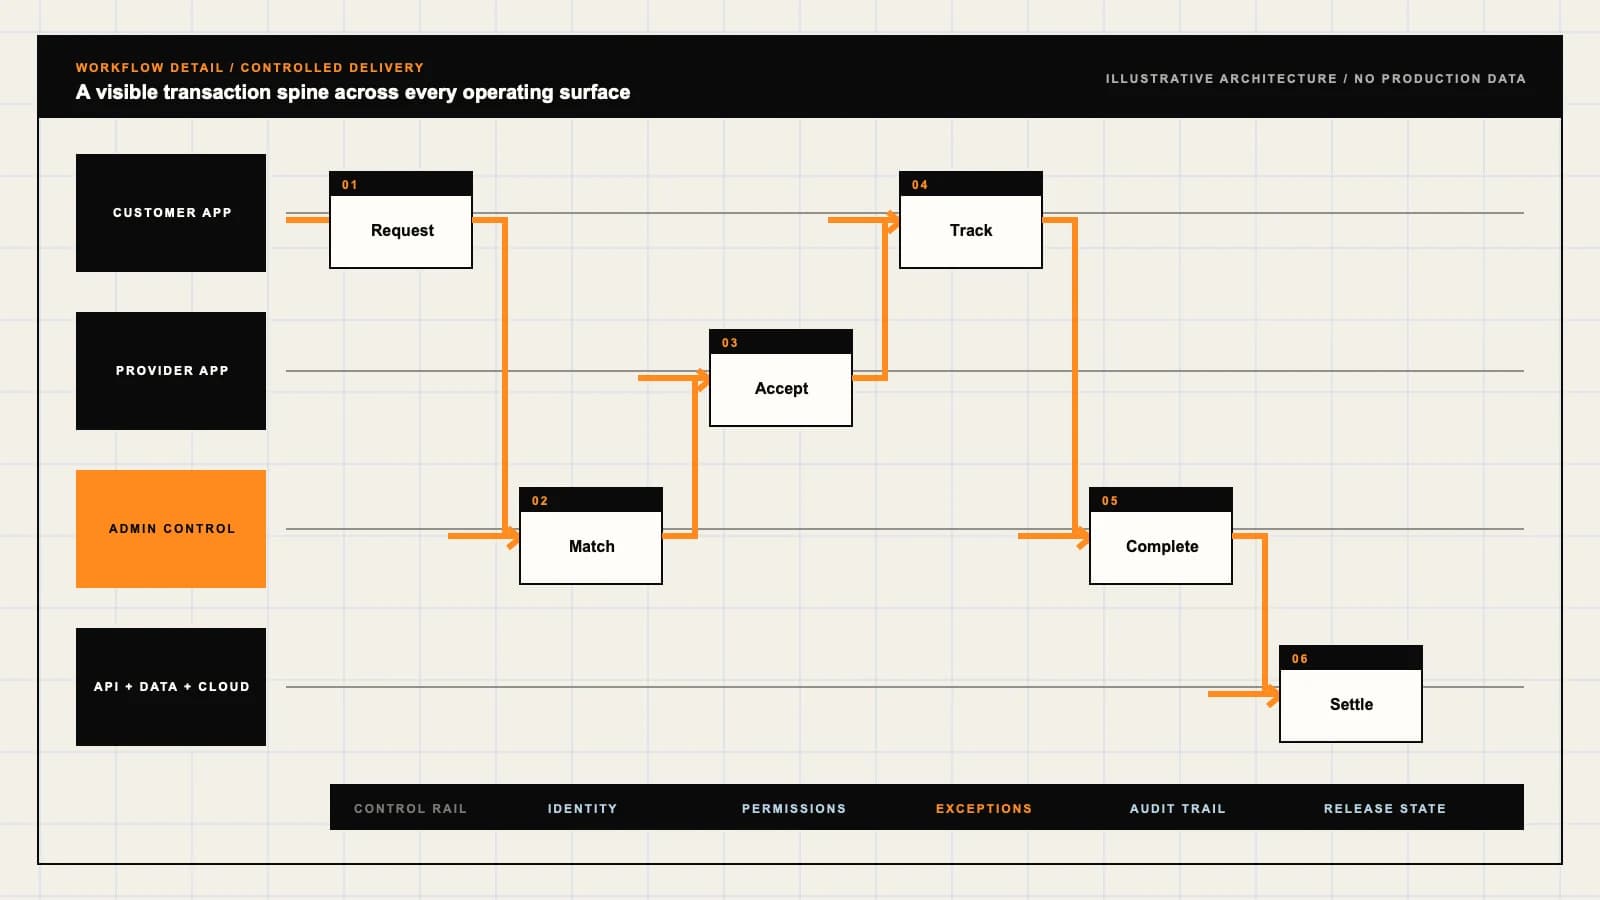
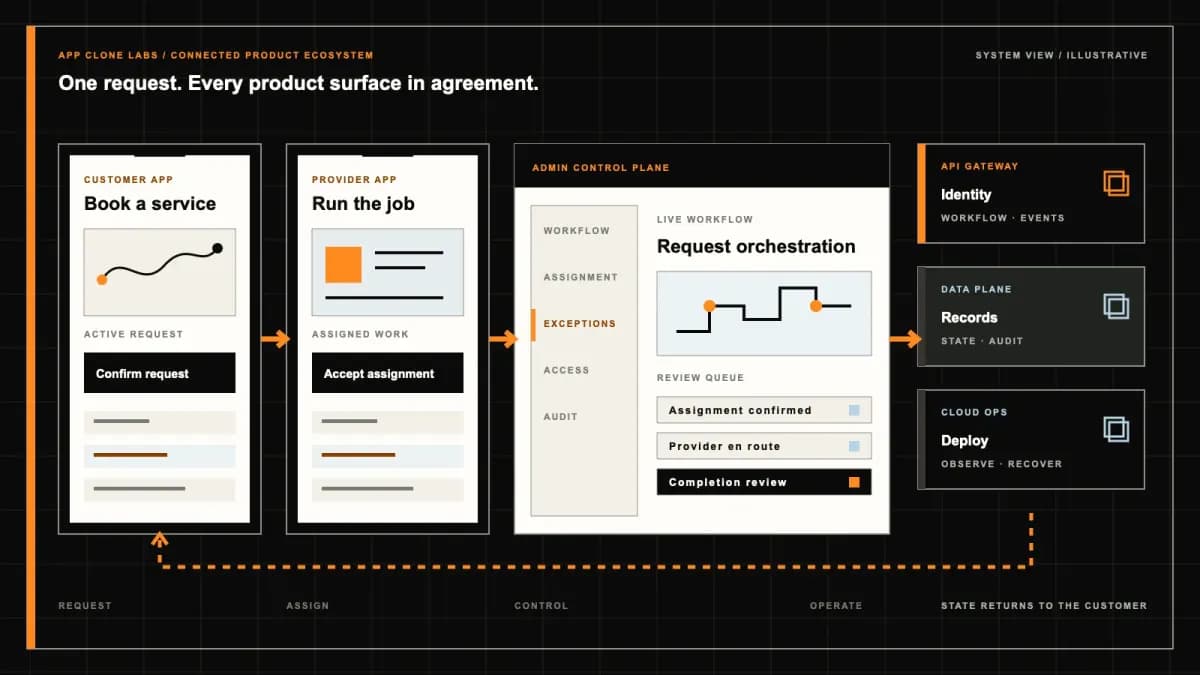
A caregiver orders medicines for a parent, books a home collection and asks for a consultation in the same session. The prescription image is unclear, the laboratory cannot cover the address and the consultation payment succeeds without a confirmed slot. One green order badge hides three unresolved responsibilities. A useful health marketplace shows which provider accepted each request, whose information is attached and which qualified person must make the next decision.
A 1mg-style health marketplace connects medicine discovery, pharmacy review, diagnostic bookings and consultation routing under an independently branded product. It is not access to Tata 1mg’s provider network, certifications, clinical team or proprietary systems. Buyers need defined operating authority and service boundaries before engineering. This page describes coordination software and buyer acceptance questions, not medical advice, permission to dispense medicines or a guarantee of clinical outcomes.
Choose the operating model before combining the catalog
An owned pharmacy channel and a marketplace of independent pharmacies have different inventory, invoicing and support responsibilities. Adding laboratories introduces collection capacity and report release; consultations introduce professional availability and clinical records. Decide which organization supplies each service, accepts the patient request and answers complaints. A shared account can simplify navigation, but it must not imply that the platform operator performs every professional service.
Compare a focused Netmeds-style pharmacy channel when dispensing and medicine fulfillment are the main business. Keep diagnostics and consultations out of the first release if their provider arrangements are not ready. Your proposal should list supported services, exclusions, required provider contracts and the evidence needed before public availability. A large category menu is not a substitute for an operable network.
Keep patient identity separate from the person paying
The account holder may be ordering for a parent, child or another person. Establish the patient identity and the authority to act for them without assuming that payment gives access to health records. Capture the necessary consent or authorization for the intended market and distinguish patient communication from payer receipts. An old saved profile should not automatically authorize a newly added caregiver to read prescriptions or laboratory reports.
At every provider handoff, carry an agreed patient identifier and enough information to resolve a mismatch. Two people with the same name cannot share a report folder. Record who supplied information, when it was changed and which request used that version. Support should be able to investigate a failed identity match without downloading the entire health history. Rehearse revoked caregiver access and a request associated with the wrong family member.
Make prescription review an accountable professional action
An uploaded document can be incomplete, unreadable, expired under applicable rules or unrelated to the selected items. Store the original submission and its provenance, then route it to the authorized pharmacy review process. Distinguish awaiting review, clarification requested, rejected and approved for specified items. Optical extraction can assist administrative entry but must not turn recognized text into clinical approval or invent a missing instruction.
The Tata 1mg authenticity reference describes pharmacist involvement in dispensing and separate quality practices for medicines and diagnostics. It is a reference to that company’s stated processes, not certification of this proposed build. Agree your own approval responsibilities, required evidence and release controls with qualified professionals. Generic marketplace support staff must not alter a pharmacist’s decision merely to clear an order queue.
Catalog restrictions must survive search, substitutions and repeat orders
A prohibited item should not become purchasable through a saved basket, a search synonym or an old promotion. Model catalog eligibility by jurisdiction, provider and service type, with a recorded review process for changes. Keep medicine identity, formulation, strength and pack details explicit where relevant to the reviewed catalog. Do not infer clinical equivalence from similar names or a lower price, and do not publish patient-specific treatment suggestions as product recommendations.
If stock is unavailable, the system needs the provider’s reviewed substitution or clarification path and any required patient approval. Preserve the originally requested item and the accepted change instead of rewriting the order. Refills require a new eligibility check under agreed rules, not automatic reuse of a historical approval. Test restricted items through mobile checkout, reorder links and administrative tools, including the attempt to replace an unavailable item with an unreviewed alternative.
Provider eligibility belongs in routing, not only onboarding
A provider can pass initial onboarding and later lose eligibility for a service or location. Store reviewed credentials, their scope, expiry and the person responsible for checking them. A decorative verified badge does not explain authority. Gate new assignments on the current record and identify accepted requests requiring reassignment or professional review when status changes. Keep the evidence restricted rather than exposing credential documents to every marketplace participant.
Separate permissions for pharmacy review, laboratory administration, report release and consultation. A staff member working across branches should not gain automatic access to all patient records. Provider offboarding needs account closure, unresolved-request ownership and treatment of retained records according to applicable obligations. Ask the demonstration to expire a credential while accepted work exists. The operator should see affected requests and an accountable resolution, not silent cancellation or unrestricted continued routing.
A diagnostic slot is not a collected or accepted sample
Home collection requires service-area coverage, provider capacity, patient matching and provider-issued preparation information. The software should present instructions supplied or approved by the laboratory rather than generate medical preparation advice. Keep requested, confirmed, collector assigned, collected and laboratory accepted distinct. A calendar confirmation alone cannot prove collection. Record rescheduling, failed access and a patient identity mismatch with a clear next action for both the customer and provider.
Link the sample identifier to the intended booking and preserve handoff events under the laboratory’s agreed procedure. An unsuitable or rejected sample needs a provider-owned recollection decision and an explanation of any billing adjustment. Do not disguise recollection as a completed test or publish a report merely because the scheduled time passed. Rehearse a collector outage and a duplicate sample update so one booking cannot acquire two unrelated results.