Healthcare and pharmacy

Lybrate-style Doctor Consultation — Custom-Built for Your Market

Clinician discovery and remote consultation marketplace. Planned for digital health operators connecting patients with licensed practitioners with role-specific workflows, operator controls, integrations, and a handover boundary defined for the selected market.

See product screens and demo access

Custom workflows

Brand-safe product strategy

Admin and operations tooling

Reference walkthrough by arrangement

Review consultation modality, consent and unanswered-request handling before agreeing the scope.

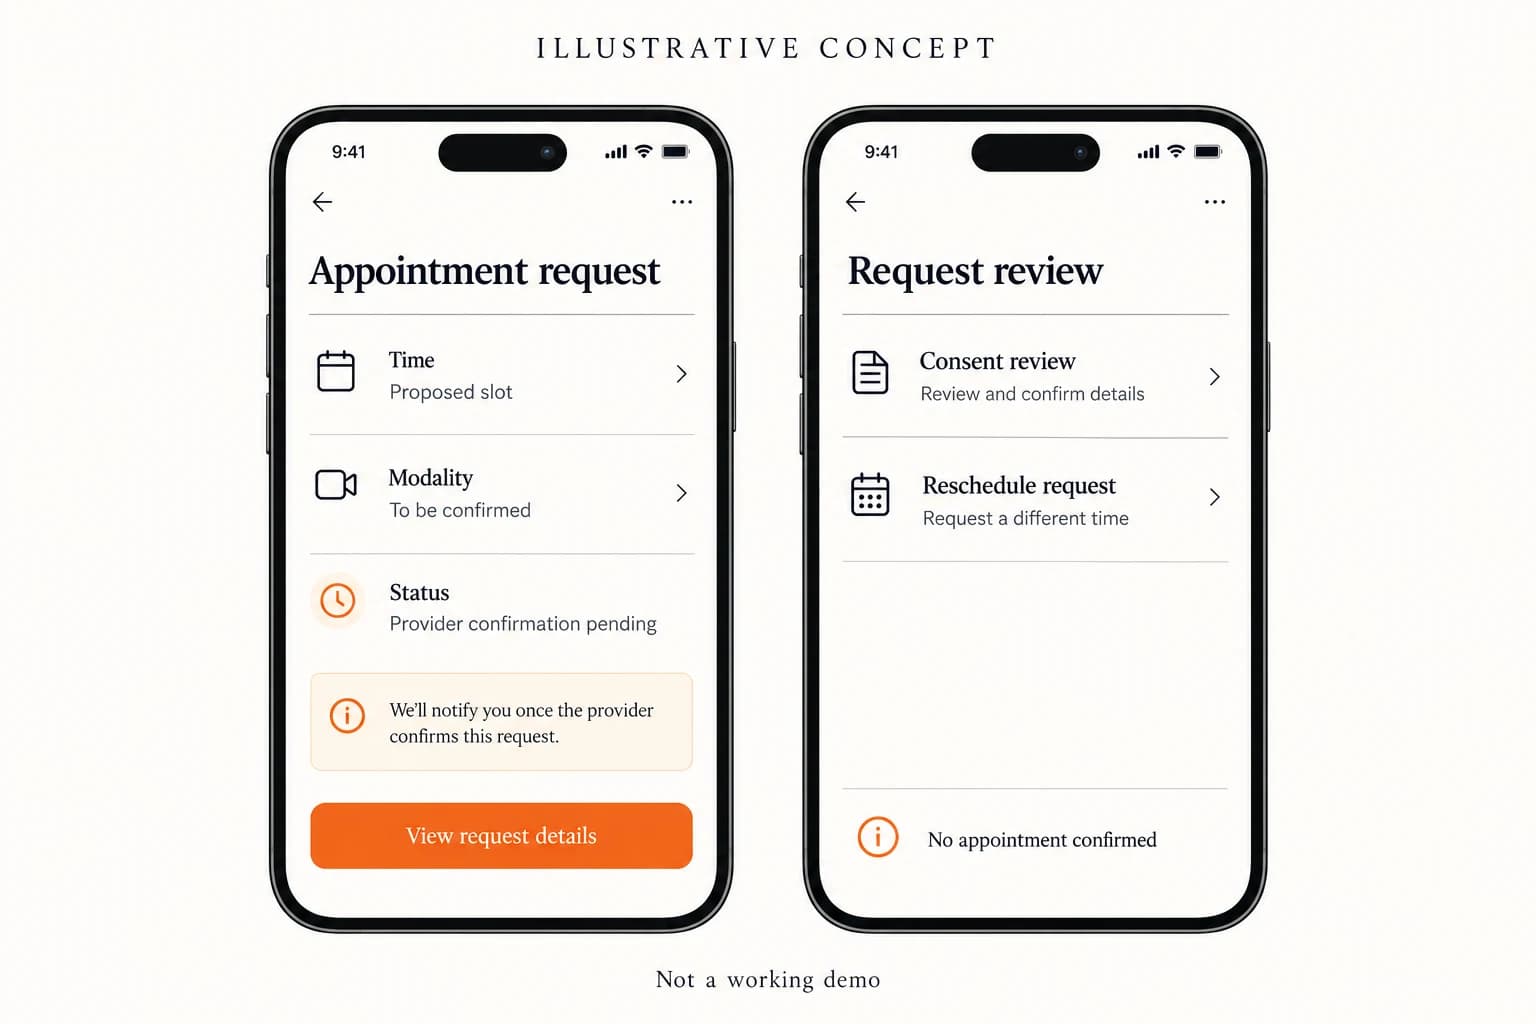
Use this original appointment-request concept to discuss a Lybrate-style consultation product. The sample modality and proposed time await provider confirmation. Ask for a working demo of the proposed request and response journey, including consent changes and referral handoffs, and agree which clinical responsibilities remain outside the booking software.

Appointment-request concept with proposed modality, time and provider confirmation pending

Appointment-request concept with proposed modality, time and provider confirmation pending

Original App Clone Labs appointment-request concept at 1536×1024, showing a sample proposed modality and time with provider confirmation pending. No names, diagnosis or personal health information are shown. This concept is not an official Lybrate interface, a completed consultation or evidence of informed consent, credential verification, medical advice quality or regulatory compliance.

What to check in the walkthrough

  • Modality and consent: Can the scoped working demo show the proposed consultation modality, applicable disclosures and consent record before a session starts? Ask to change the modality or withdraw consent, inspect the version and time of the recorded choice and demonstrate how customer and provider receive the revised request using synthetic data.
  • Referral handoff: How would a provider decline the requested modality or recommend an in-person referral? Ask to demonstrate the authorized handoff, customer acknowledgement, restricted record access and the boundary between booking support and clinical decisions; identify who owns the next action without implying that the platform makes a diagnosis.
  • Response states: Can the working demo distinguish awaiting confirmation, accepted, unanswered, expired, cancelled and completed requests? Ask to interrupt a session and replay a late provider response, then inspect timeout rules, customer updates, any applicable payment adjustment and the escalation owner so an unanswered request cannot appear completed.
Open full-size reference

Solution reference register

01 / Reference and IP

This page references third-party product names only to describe familiar product models and planning references. App Clone Labs is not affiliated with or endorsed by those brands. Build decisions require independent legal, regulatory, and operational review for your market.

02 / Artifact status

Boards, diagrams, screens and workflow descriptions on this page are illustrative planning artifacts, not evidence of a deployed client product.

03 / Regulatory caveat

Qualified healthcare concept · Clinical licensure and telehealth rules vary by market · Not an emergency service · Health-data consent and retention review required

04 / Rights and handover

Source access, licensing, repositories, environments, documentation, acceptance and handover are defined by the signed contract and accepted scope.

Scope

Operating model defined

Roles, workflows, dependencies, exclusions, and assumptions are made reviewable.

Evidence: illustrative

System

Applications connected

Experience, operations, services, data, integrations, and release controls are planned together.

Evidence: illustrative

Handover

Rights stated in writing

Access, assignment, licensing, dependencies, documentation, and support follow the signed agreement.

Evidence: illustrative

Artifact register

Product screens and planning references.

Reference screens illustrate workflows, not a contracted feature list. Sample prices, data, and responses are demonstration content; confirm the current scope during a walkthrough.

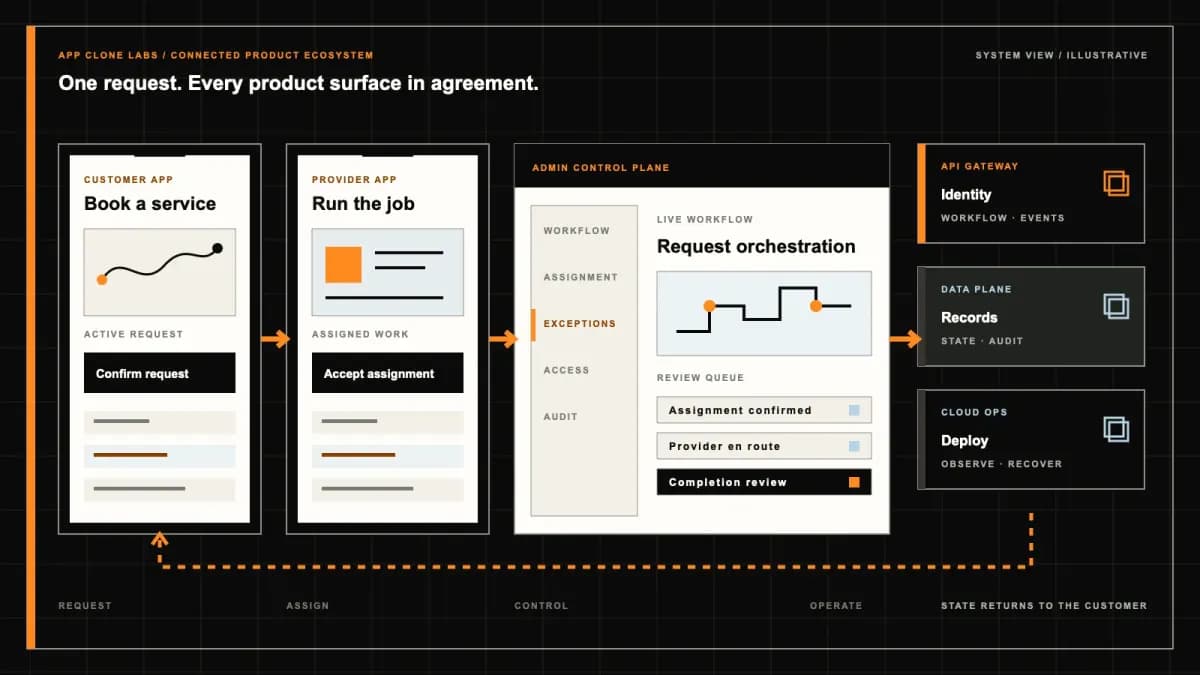
Lybrate-style Doctor Consultation connected product workflow planning visual
Connected customer, operations, and data workflowEvidence: illustrativeOpen full-size reference
Lybrate-style Doctor Consultation product engineering ecosystem visual
Product engineering ecosystem and handover boundaryEvidence: illustrativeOpen full-size reference

A paid consultation request is not yet an accepted clinical appointment

A patient pays for a consultation, uploads a report and waits. The practitioner has not accepted the request, the calendar shows a tentative slot and support can only see that money was collected. The product has confused three events: payment, availability and clinical acceptance. A useful consultation platform makes each event visible and gives an unresolved request an owner before the patient is left refreshing a chat window.

A Lybrate-style consultation solution connects patients with independently verified practitioners through agreed remote-care channels. The software must distinguish public information, private asynchronous exchanges and scheduled live consultations. This is independently branded engineering, not access to Lybrate’s practitioners, records, proprietary platform or clinical operation. Buyers should establish who provides care, where that person may practise and which requests the service can responsibly accept before comparing screen designs.

Give each consultation channel a different service promise

The official Lybrate terms distinguish general information, private interactions and appointment scheduling. That separation is useful for planning the product, but it does not transfer that operator’s commercial terms or professional responsibilities to your business.

A public question should not create the impression of an individualized clinical relationship. An asynchronous consultation needs a defined response arrangement and clear status when the practitioner has not yet replied. A scheduled call needs a confirmed time, participant instructions and recovery from connection failure. Do not label all three options “instant consultation.” Choose the initial channel based on the operator’s real staffing and reviewed clinical scope, then explain its limits before taking payment.

Verify professional authority before showing bookable availability

A profile photograph and uploaded certificate are not a completed credential review. Record which registration information was checked, the reviewer, its provenance and the permitted scope for the intended market. Keep self-reported biography separate from verified facts. Eligibility can change after onboarding, so a renewal failure needs an explicit rule for new requests and already confirmed appointments. Paid participation must not purchase a verification decision.

The appointment also depends on the patient’s location and the practitioner’s applicable authority, not simply the country selected during account creation. Qualified clinical and legal reviewers should define the operating boundaries and any restrictions on remote consultation. Make unavailable services unavailable in the booking flow rather than relying on a disclaimer beneath checkout. Rehearse an eligibility suspension while a patient has an appointment pending and show who coordinates a suitable next step.

Ask for enough intake without building an unnecessary medical archive

A short consultation request does not justify collecting every historical report before a practitioner has reviewed suitability. Define required intake with clinical owners and explain why each sensitive field is requested. Let patients distinguish an unanswered question from a confirmed negative answer. Uploaded documents need a patient association, file checks and restricted access; a familiar filename is not evidence that the report belongs to the person being consulted.

Show patients which attachments will be shared with the selected practitioner and how they can correct a mistaken upload. A support agent investigating a failed payment should not automatically receive the full medical file. Separate operational status from clinical content in the console. Test a wrong document, a rejected upload and a consultation reassigned with consent. Previously granted access must not remain open merely because a provider once appeared in the request history.

Reserve a live slot without turning stale calendars into double bookings

A calendar result is a proposal until the booking system confirms capacity. Use an identifiable hold and an acceptance rule that handles simultaneous requests, payment delay and clinic-side calendar changes. Make the patient’s time zone and the practitioner’s local appointment time legible. Reminders must reflect the current confirmed appointment, not an earlier slot that survived in a notification queue after rescheduling.

A call link should authorize the correct participants for the correct session. Decide what happens if either person arrives late, cannot connect or needs an accessibility accommodation. Do not convert a failed video appointment into an asynchronous consultation without agreement on the changed service. Preserve the original booking and the accepted amendment. The buyer should inspect these transitions on both screens and in the coordinator queue, not only watch a successful video connection.

An asynchronous message needs a queue owner, not a green presence dot

A practitioner appearing online does not establish that a paid request has been accepted or that someone is continuously monitoring messages. Define assignment, acceptance, response arrangements and escalation for an unanswered request. Show whether a message is sent, delivered or awaiting professional review without implying that a read indicator proves clinical assessment. Prevent an abandoned conversation from remaining indefinitely labelled as active care.

Follow-up access needs a stated boundary: what period or issue is covered, who may respond and when a new consultation is required. Preserve the thread when a practitioner becomes unavailable, but do not silently transfer private records to another professional. A coordinator can arrange an approved handover without impersonating the practitioner. Test delayed replies, reassignment refusal and messages arriving after closure. Patients should understand the next action without relying on hidden staff knowledge.

The official Lybrate privacy policy describes health information in private practitioner interactions. It illustrates why these records need distinct handling; it is not a privacy notice or legal approval that another service can adopt unchanged.

Review consultation consent, sensitive-data processing, vendor access and retention for the intended jurisdiction. Optional call recording needs its own deliberate decision, participant explanation and access limits rather than being silently enabled by a communication provider. Marketing permission must remain separate from care access. Record the notice version and the meaningful action taken, while supporting appropriate access and correction requests. A generic checkbox does not settle every purpose for which the operator might later want to use medical information.

Include backups and exports in the records policy. A deleted attachment should not remain casually available through a support download or an old session link. Establish how retention obligations, correction requests and restricted investigation records are handled by authorized staff, including when a communication vendor holds another copy.
A family booking must identify the patient and the representative separately

The account holder may book for a parent or child, but that does not mean every household member can read every consultation. Keep patient identity distinct from payer and booking representative. Qualified reviewers should define authority checks, age-related rules and when the practitioner needs to confirm who is present. A shared telephone number cannot be the only basis for joining histories or releasing records.

Representative permissions may expire or be withdrawn while a booking remains valid. Define which operational notices the representative receives and which clinical information stays restricted. Avoid exposing sensitive details through lock-screen reminders, shared email receipts or a family dashboard. Rehearse a payer requesting a private transcript and a patient removing a representative. The coordination team needs a documented decision path, not an informal assumption that whoever paid controls the medical record.

Keep urgent-care redirection separate from ordinary support escalation

The service is not an emergency service. Clinical owners should define clear exclusions and appropriate redirection language before requests enter a routine response queue. Software may show reviewed instructions and route concerns to designated staff; it must not claim to diagnose an emergency or guarantee timely professional intervention. Make the limitations visible at the point where a user could otherwise mistake the platform for immediate assistance.

Operational support must know when its authority ends. A missed call, a billing complaint and a reported clinical concern require different owners and access. Refund processing must not close a clinical complaint automatically. Document the operator’s escalation coverage and what happens outside it without promising round-the-clock care unless that service is actually established. Test an excluded request and a concern raised after consultation closure using reviewed scenarios, not real patient data.

Reconcile consultation fees without rewriting what care was delivered

Payment authorization, practitioner acceptance, session completion and payout are separate events. Disclose the consultation fee, any platform charge and the operator’s cancellation terms before commitment. Review professional fee and commercial arrangements locally rather than copying another platform’s fee split. If a payment result is uncertain, reconcile the provider outcome before retrying; a second charge is not a reasonable substitute for an exception queue.

An interrupted session may need a reconnection, rescheduling or refund review under the agreed policy. It does not justify deleting clinical documentation or changing a completed encounter into a session that never existed. Keep financial adjustments traceable and restrict who can make them. Demonstrate a duplicate callback, practitioner non-attendance and a partial connection. The practitioner’s clinical judgment and the platform’s payment decision should remain distinguishable in every record.

Choose consultation depth before adding a broader care directory

Compare the Practo-style care-discovery model when the buying priority is clinic search, in-person appointments and practice coordination. The consultation-led page focuses instead on acceptance, private communication and accountable follow-up. They can share selected infrastructure without presenting the same service promise.

Start with a practitioner group and consultation mode that the operator can supervise. Laboratory ordering, pharmacy fulfilment and continuing care programs introduce different responsibilities and should not appear included merely because the reference brand offers adjacent services. Agree provider contracts, data flows and staffing before expansion. A narrower, clearly operated service is more useful to the buyer than a long menu whose clinical and operational ownership has not been decided.

Validate the consultation journey with controlled patient scenarios

Illustrative screens explain intended interfaces; they are not proof of available practitioners, authorized clinical integrations or an established care service. Request a sandbox walkthrough using fictional patient records. Inspect stale availability, credential suspension, delayed messages, consent withdrawal, wrong attachments and failed connections. Buyer acceptance should include keyboard navigation, readable mobile consent and permission checks across patient, practitioner and coordinator views.

The scope should identify configured components, new engineering, licensed services, operational duties and launch exclusions. Establish review owners for clinical boundaries, privacy, accessibility and incident handling. Do not accept automated summaries or apparent session completion as evidence of diagnosis, treatment quality or guaranteed outcomes. Handover should include the agreed source package, deployment access, operational documentation and access-control instructions under the contract.

Bring an example consultation request to a confidential product-scope discussion so the team can map acceptance, availability, consent and recovery before choosing the implementation.

Use the delivery process to set clinical-owner review, restricted-record testing and coordination rehearsal checkpoints before public launch.

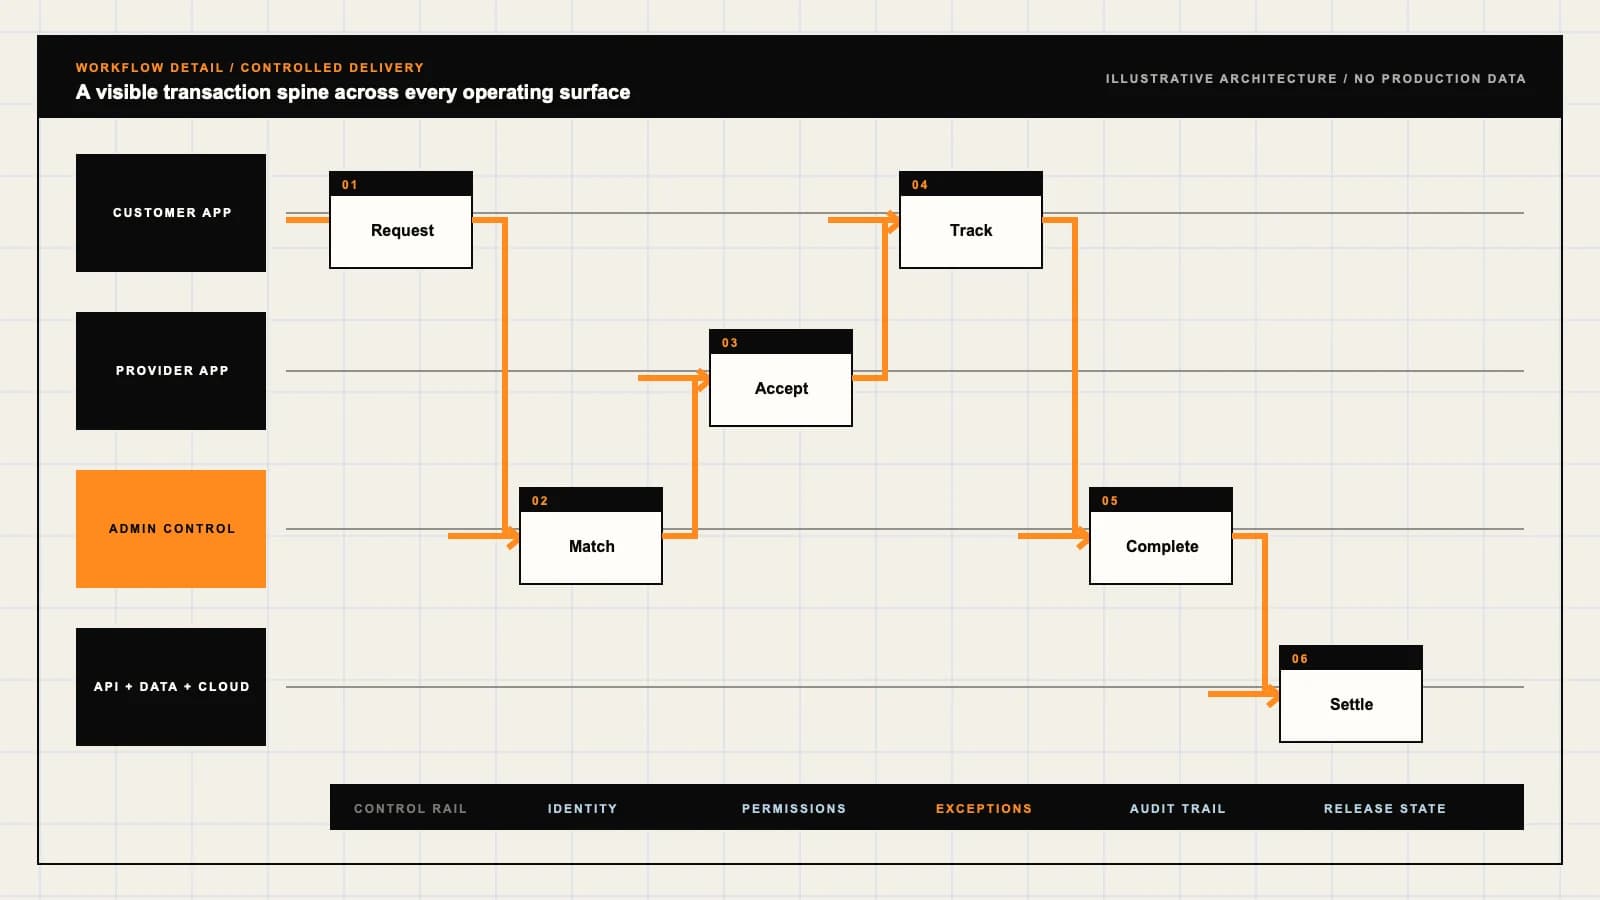
Product flow

Role-workflow flow diagram.

A visual map of how each role interacts with each workflow stage, with operator controls and integration boundaries.

Deployable Product Architecture

Lybrate-style Doctor Consultation

SEPARATE AN INQUI…PROTECT THE APPOI…RECORD WHAT WAS D…Request the right…Accept work withi…Resolve access fa…INTEGRATIONS: Practitioner credential and scheduling systems with reviewed registry acces…OPERATOR CONTROLS: Verify authority beyond a profile badge · Make sensitive access purpose-spe…
Illustrative validation artifact — role-workflow flow diagram; final surfaces, boundaries, and integration topology are confirmed during discovery.

User roles

Lybrate-style Doctor Consultation roles and workflows.

Clone-inspired platforms usually need several coordinated interfaces, not just a customer app.

Patient or authorized representative

01

Request the right consultation mode

Choose a practitioner and submit the minimum relevant intake. Understand whether the request is awaiting acceptance, scheduled for a live session or assigned to an asynchronous response queue.

Verified practitioner

02

Accept work within reviewed clinical authority

Review patient identity, location, consent and consultation suitability. Manage availability and document professional decisions without treating a paid request as an obligation to provide unsuitable remote care.

Care coordination

03

Resolve access failures without making clinical decisions

Handle scheduling, missed connections, payment uncertainty and record-access requests. Route clinical concerns to authorized professionals and keep support access limited to its legitimate purpose.

Workflow

Lybrate-style Doctor Consultation workflow stages.

Each workflow stage is mapped to a role, screen, API, notification, admin control, and measurable launch outcome.

Request

01

Separate an inquiry from an accepted consultation

Present the practitioner, mode, fee, expected response arrangement and service limits. Capture appropriate consent and route unsuitable requests according to a clinically reviewed policy.

Connect

02

Protect the appointment or response commitment

Confirm capacity before accepting the request. Recover a failed call or delayed response without charging twice, exposing attachments or silently moving the patient to another practitioner.

Close and follow up

03

Record what was delivered and what remains open

Keep clinical documentation, follow-up entitlement, payment outcome and support complaints distinguishable. Give each unresolved item an accountable owner and permission boundary.

Deployable Product Architecture

Workflow / system register

Revision FPlanning surface

Care workflow

Lybrate-style Doctor Consultation workflow stages.

Access and accountability travel with the record

Care workflow: Lybrate-style Doctor Consultation workflow stages.Access and accountability travel with the record. Role boundaries, consent, and traceability shape every interaction.
01

Separate an inquiry from an accepted consultation

02

Protect the appointment or response commitment

03

Record what was delivered and what remains open

Control note

Role boundaries, consent, and traceability shape every interaction.

Illustrative architecture register; validate against the accepted scope.

Operator controls

Lybrate-style Doctor Consultation admin and operator controls.

The control center is scoped as a first-class product surface, not an afterthought.

Practitioner eligibility

01

Verify authority beyond a profile badge

Record credential provenance, review status, permitted scope and renewal requirements. Suspend new bookings when eligibility changes while coordinating already scheduled patients.

Consent and records

02

Make sensitive access purpose-specific

Separate consultation consent, recording choices, representative authority and marketing permission. Restrict clinical attachments, messages, exports and administrative access with traceable actions.

Clinical boundaries

03

Keep urgent needs out of an ordinary response queue

Use clinician-reviewed service exclusions and redirection language. The software does not diagnose, guarantee treatment or replace local emergency services.

Monetization

Lybrate-style Doctor Consultation monetization models.

We model monetization early so payments, admin controls, and reporting support the business.

Disclose the paid service before commitment

Show the practitioner fee, any separate platform charge and relevant cancellation terms. Review fee arrangements for the jurisdiction rather than copying another operator’s percentages.

Charge for administration without implying clinical endorsement

Offer scheduling or practice-management features with defined permissions. A paid subscription must not become a verification badge or a promise of better medical outcomes.

Keep promotion away from private clinical decisions

Disclose commercial placement and review health claims. Sponsorship must not authorize access to consultation records or purchase a recommendation in the patient’s private session.

Integrations

Lybrate-style Doctor Consultation integration surface.

External systems that determine launch readiness, data flow, and operational continuity.

Integration

01

Integration 1

Practitioner credential and scheduling systems with reviewed registry access, eligibility expiry, appointment holds and conflict reconciliation

Integration

02

Integration 2

Secure messaging and live-session providers with participant authorization, attachment controls, connection recovery and explicit recording settings

Integration

03

Integration 3

Payment and clinical-record systems with consultation identifiers, restricted exports, uncertain-payment review and documented retention responsibilities

Scope drivers

Lybrate-style Doctor Consultation scope drivers.

The variables that most influence build effort, cost, and launch readiness.

Clinical operating model

01

Define who is responsible for remote care

Agree the target jurisdiction, patient populations, practitioner authority, service exclusions and clinical governance before selecting consultation channels.

Communication commitment

02

Choose asynchronous or scheduled care deliberately

Define queue ownership, response arrangements, session duration and follow-up boundaries. Different modes need different availability and refund rules.

Health information

03

Decide what must be collected and retained

Map intake, attachments, messages and practitioner notes to purpose, access and retention. Review representative access, vendors and cross-border handling with qualified specialists.

Deployable Product Architecture

Scope drivers / system register

Revision EPlanning surface

Care workflow

Lybrate-style Doctor Consultation scope drivers.

Access and accountability travel with the record

Care workflow: Lybrate-style Doctor Consultation scope drivers.Access and accountability travel with the record. Role boundaries, consent, and traceability shape every interaction.
01

Define who is responsible for remote care

02

Choose asynchronous or scheduled care deliberately

03

Decide what must be collected and retained

Control note

Role boundaries, consent, and traceability shape every interaction.

Illustrative architecture register; validate against the accepted scope.

V1 scope

Lybrate-style Doctor Consultation V1 foundation.

Launch the smallest complete operating loop first, then scale the product with confidence.

One supervised consultation service

01

Prove request acceptance before broadening specialties

Launch a reviewed practitioner group, patient eligibility policy and communication mode. Keep professional authority and service limitations visible throughout the journey.

Connection and scheduling recovery

02

Test failure with both participant screens

Handle stale slots, absent participants, delayed responses and interrupted calls. Preserve the consultation identifier and avoid duplicate booking or payment.

Restricted records and coordination

03

Give support useful facts without unrestricted medical access

Provide permissioned status views, controlled attachments and an exception queue. Rehearse representative access and an incorrectly uploaded document.

Later phases

Lybrate-style Doctor Consultation post-launch expansion.

Capabilities that should usually wait until real usage proves the core loop.

Additional specialties

01

Review clinical suitability before expanding the directory

Each specialty may change intake, remote-care limits and escalation needs. Do not assume a successful consultation flow transfers unchanged to every clinical discipline.

Longitudinal care programs

02

Agree continuing responsibility and consent

Add follow-up plans only after ownership, availability, information sharing and discontinuation arrangements are defined by the clinical operator.

Connected clinic workflows

03

Extend beyond remote consultation under separate scope

In-person scheduling, laboratory connections and practice tools require their own provider agreements, data boundaries and operational acceptance checks.

Deployable Product Architecture

Later phases / system register

Revision FPlanning surface

Care workflow

Lybrate-style Doctor Consultation post-launch expansion.

Access and accountability travel with the record

Care workflow: Lybrate-style Doctor Consultation post-launch expansion.Access and accountability travel with the record. Role boundaries, consent, and traceability shape every interaction.
01

Review clinical suitability before expanding the directory

02

Agree continuing responsibility and consent

03

Extend beyond remote consultation under separate scope

Control note

Role boundaries, consent, and traceability shape every interaction.

Illustrative architecture register; validate against the accepted scope.

Regulatory review

Lybrate-style Doctor Consultation regulatory and compliance flags.

Each flag must be reviewed by qualified counsel for your target market before build or launch.

Flag 1

Qualified healthcare concept

Flag 2

Clinical licensure and telehealth rules vary by market

Flag 3

Not an emergency service

Flag 4

Health-data consent and retention review required

Reference walkthrough

Request a Lybrate-style Doctor Consultation reference walkthrough.

Ask us to confirm which reference surfaces are currently available for this product model. Rather than publishing shared demo credentials, we schedule a private guided walkthrough for qualified buyers.

Reference surface

01

Patient or authorized representative: Request the right consultation mode

Request a role-specific demonstration and confirm which capabilities are currently available. Review the proposed responsibility: Choose a practitioner and submit the minimum relevant intake. Understand whether the request is awaiting acceptance, scheduled for a live session or assigned to an asynchronous response queue.

Reference surface

02

Verified practitioner: Accept work within reviewed clinical authority

Request a role-specific demonstration and confirm which capabilities are currently available. Review the proposed responsibility: Review patient identity, location, consent and consultation suitability. Manage availability and document professional decisions without treating a paid request as an obligation to provide unsuitable remote care.

Reference surface

03

Care coordination: Resolve access failures without making clinical decisions

Request a role-specific demonstration and confirm which capabilities are currently available. Review the proposed responsibility: Handle scheduling, missed connections, payment uncertainty and record-access requests. Route clinical concerns to authorized professionals and keep support access limited to its legitimate purpose.

Next step

04

Book a walkthrough

Request a live, private walkthrough of the reference implementation. We will confirm scope and discuss configured deployment versus custom build for your market.

Open register

Deployable Product Architecture

Reference walkthrough / system register

Revision APlanning surface

Care workflow

Request a Lybrate-style Doctor Consultation reference walkthrough.

Access and accountability travel with the record

Care workflow: Request a Lybrate-style Doctor Consultation reference walkthrough.Access and accountability travel with the record. Role boundaries, consent, and traceability shape every interaction.
01

Patient or authorized representative: Request the right consultation mode

02

Verified practitioner: Accept work within reviewed clinical authority

03

Care coordination: Resolve access failures without making clinical decisions

04

Book a walkthrough

Control note

Role boundaries, consent, and traceability shape every interaction.

Illustrative architecture register; validate against the accepted scope.

Process

A traceable path from decision to acceptance.

  1. 01

    Model teardown

    We map the reference business model, user roles, monetization path, regulatory needs, and launch constraints.

    Artifact: Product teardown, risk map, role matrix

  2. 02

    Market-fit blueprint

    We reshape the model around your market, operations, pricing, workflows, and first release priorities.

    Artifact: Feature scope, flows, technical plan

  3. 03

    Design and build

    Product, design, engineering, QA, and cloud delivery move in weekly demo cycles with visible progress.

    Artifact: Working releases, QA notes, sprint demos

  4. 04

    Launch and operate

    We support production release, monitoring, handoff, roadmap decisions, and post-launch improvement.

    Artifact: Launch checklist, docs, growth backlog

FAQ

Questions to resolve before the build.

01Does this include Lybrate’s practitioners or patient records?

No. It is independently branded software. Another company’s practitioner network, patient information, proprietary implementation and clinical operation are not included.

02Is payment enough to confirm a consultation?

No. Payment, practitioner acceptance and appointment availability are distinct events. Show each status and define who resolves a paid request that has not been accepted.

03How is asynchronous consultation different from a live call?

Asynchronous work needs assignment, response arrangements and follow-up boundaries. A live call needs confirmed capacity, participant access and connection recovery. Changing modes requires clear agreement.

04What does practitioner verification cover?

The operator must define credential provenance, permitted scope, reviewer responsibility and renewal checks for the market. A profile badge or paid participation does not establish professional authority or guarantee care quality.

05Can a patient book for a family member?

The model can support reviewed representative access. Identify the patient separately from payer and account holder, establish authority and limit clinical-record visibility appropriately.

06Do calls have to be recorded?

No recording is implied. Decide whether it is appropriate, review consent and retention requirements, explain the choice and restrict access. A vendor default should not silently determine the policy.

07Can support staff read all consultation messages?

Not by default. Separate operational status from clinical content and grant minimum necessary, purpose-specific access with traceable actions and appropriate review.

08What happens if the practitioner does not reply?

Define queue ownership, response arrangements, patient communication and reassignment or financial review. Do not imply continuous monitoring through a presence indicator.

09Can the software diagnose or provide emergency care?

No. It is not an emergency service and does not diagnose or guarantee treatment. Qualified clinical owners must establish suitability, exclusions and redirection arrangements.

10Is legal or clinical compliance guaranteed?

No. Practitioner authority, telehealth restrictions, professional fees, consent and health-data handling require qualified review for the intended jurisdiction and operating model.

11Are pharmacy and laboratory services included?

Not automatically. They introduce separate provider agreements, fulfilment processes and information-sharing responsibilities and require explicit scope and review.

12What should the buyer test before acceptance?

Use fictional records to inspect stale slots, suspended credentials, wrong attachments, delayed messages, failed calls, representative permissions, consent changes and duplicate payment events across all participant views.

Primary sources

References behind this page

Dated official documentation, standards, and research that support the factual claims on this page.

  1. 01
  2. 02

Citation readiness

How to interpret this page

Published by App Clone Labs Editorial Team

Commercial claims
Scope, cost, and timeline claims are planning guidance and require validation in a current proposal.
Evidence status
Diagrams, boards, examples, and estimates are illustrative planning artifacts unless explicitly identified with a source and measured evidence status.

Next decision

Turn the brief into an accepted product scope.

Define outcomes, constraints, evidence, rights and handover before delivery begins.

Commercial rights, repositories, environments, documentation, acceptance and handover remain contract-defined.

Scope Lybrate-style Doctor Consultation

Independent from Lybrate

App Clone Labs is an independent software development studio. We are not affiliated with, connected to, sponsored by, or endorsed by Lybrate.

Why this name appears

Lybrate is referenced descriptively to identify familiar product mechanics and common search terminology. “Clone” describes a planning reference, not a replica.

Original delivery

Any product delivered by App Clone Labs is independently designed and developed for the accepted scope. It does not contain proprietary code, branding, copy, interface assets, or confidential material from Lybrate.

Trademark ownership

Lybrate and associated names, logos, and marks remain the property of their respective owners. Their use identifies a reference category and does not imply authorization or endorsement.